Saturday, May 28, 2011

3D Evaluation of Root Canal Morphology (Cone Beam Computed Tomography)

At Superstition Springs Endodontics, the use of cone beam computed tomography (CBCT) is a valuable tool in endodontic diagnosis and treatment. This technology is used on a case by case basis, following the guidelines specified in the joint position statement by the AAE and AAOMR.

The joint position statement by the AAE and AAOMR regarding the use of CBCT in endodontics states that "The patient’s history and clinical examination must justify the use of CBCT by demonstrating that the benefits to the patient outweigh the potential risks. Clinicians should use CBCT only when the need for imaging cannot be answered adequately by lower dose conventional dental radiography or alternate imaging modalities."

A significant concern noted in this position statement is the added radiation dosage to the patient. In our practice, using the J. Morita Veraviewepocs 3De, the patient is exposed to the lowest radiation dose on the market. A single 40 x 40mm 3D scan exposes the patient to 0.029mSv. This is approximately the same amount of radiation a patient would receive with 9 digital periapical films (0.003mSv).

The volume of data acquired in a single scan allows us to look at that tooth from any coronal, sagittal or axial view, and the ability to re-slice the volume at any slice thickness. This volume of data can be manipulated over and over to gather unlimited amount of information about the tooth and it's periapical tissues.

A CBCT scan, provides visualization of root number & anatomy, canal number & morphology, much more accurate evaluation of peripical tissues. Understanding the advantages of CBCT, the limited radiation and limited liability associated with a focus field CBCT, I would suggest that the benefits routinely outweigh the potential risks. Unfortunately, there are often benefits of a CBCT scan that are not apparent unless the scan is taken. The following case is an example.

This patient presented with complaint of pain in lower left quadrant. Recent crown prep on #19. Regular diagnostics were inconclusive as to the source of this pain (#19 was testing normally to vitality, probing and percussion testing) A short obturation of #18 was noted, but this tooth was asymptomatic. After short period of time waiting to see if symptoms localized, and failure to do so, a CBCT scan was acquired to evaluate if there was apical bone loss associated with one of these teeth that would help in the diagnosis.

CBCT did not show any radiographic lesions on #18 or #19. The temporary crown #19 was removed for additional pulpal testing. Tooth #19 gave no response to cold on the buccal side and a vital response on the lingual side. It was decided that endodontic treatment should be initiated on #19 with a probable "partially necrotic" pulp.

The CBCT gives us valuable information about tooth #19. For example, following CBCT, prior to starting RCT #19, we know that the mesial root is a single root with 3 canals that merge. We also know that distal root has a single canal.


3 canals found in a single, mesial root. This was identified prior to treatment with CBCT. In this particular case, the 3rd (middle) canal would likely not have been found due to its location.


In this case, the CBCT identified a variation in the mesial canal morphology. Knowing that the mesial root was a single root and that it had 3 canals, gave me the ability & confidence to explore the ML-MB groove to a greater depth than would have normally been done for fear of perforation. This is a perfect example of radiographic information that is not available through traditional 2D imaging. This information allowed us to provide better cleaning, shaping and obturation, which will lead to a better RCT.

Friday, May 6, 2011

Endodontic Retreatment - Another Tooth Saved!

DX: Prior RCT w/ Chronic Apical Abscess
Huge periapical lesion noted. A thin, short (mesial) and long (distal) obturation.
Retreatment recommended.

Retreatment completed.

4 month initial healing seen.

2 yr recall shows fantastic healing. This tooth could easily have been condemned and extracted initially. Proper diagnosis, and ability to improve the cleaning, shaping and obturation allowed this tooth to be saved. Endodontists are specialists in saving teeth.


Thursday, March 24, 2011

CBCT to Evaluate Apical Lesions

We have been discussing the use of CBCT in the practice of endodontics. There have been questions about whether CBCT is really necessary, or just another cool image. That particular question was one of the biggest we had in our decision to move to CBCT. We also ask that question to ourselves when we recommend a CBCT scan to our patients. However, much like a microscope, until you look through the scope, you often don't know what you are missing. I have found that quite regularly, I will find things that I could not have seen otherwise and it has changed the treatment that I have recommended.

Here's an example of a routine CBCT scan that I did prior to endodontic surgery. This scan gave me added information, that then changed the treatment plan and give us better prognosis.

This patient presented for evaluation. The teeth are asymptomatic, but a lesion seen by his general dentist. The lesion is obviously on the MB root of #3, with ledged MB canal. The crown margins looked good and since the MB canal is ledged, we were planning to treat this tooth with an apicoectomy. I recommended a routine, pre-surgical CBCT to evaluate the root anatomy, sinus proximity and buccal bone contours.


This slice through the MB root shows that there is a missed MB#2 canal.

A slice through the palatal root shows a periapical lesion on the palate not visible in the original, pre-op radiograph. This now changes our treatment recommendation. An apicoectomy will resolve the MB issues, but fail to resolve the palatal lesion. This could cause continued problems and lead to the assumption of a failed endodontic surgery, when the palatal root could be the problem.

An additional slice through the palatal roots shows that #2 also has a significant periapical lesion requiring treatment.

A sagittal view of #2 again shows the extent of the lesion.

While the lesion on the palate of #2 is visible in the original radiograph, there is no doubt about it's presence with the sagittal view above.

In this case the additional information about the palatal lesion on #3 changed the treatment recommendation and will thereby improve the prognosis. Lack of CBCT scan in this case would have led to wrong treatment recommendation.

That being said, I know there are those who will say..."alway retreat first" and you don't need a CBCT scan to make that decision.

CBCT provides improved imaging of the the teeth and periapex. I welcome the added information into the diagnostic and treatment part of my practice. For more information about the application of CBCT into endodontics, the upcoming Inner Space Seminar is right around the corner.

Tuesday, March 8, 2011

Implant Training by Mentorship!!!!????

I think we all agree that continuing education is one of the foundations of every profession.

It guarantees that practitioners remain up to date and abreast of new techniques, materials and research studies that are continuously changing and improving.
With that in mind, I have noticed a trend in the past two years that in my opinion is alarming, if not outright dangerous for the dental profession.

Recently many, for profit, seminar groups, institutes and other continuing education providers are marketing so called “Implant Mentorship courses”. Most of these courses are 2-4 days. Most faculties are general dentists and they claim they provide training for implant placement and restoration in that time period, through “mentoring”.
As an educator and a practitioner; I believe these kinds of so called “training”, will only give a false sense of knowledge and competence to people attending them.
The advances in implant dentistry have been wonderful for patients who are missing one or more teeth. In my opinion, any general dentist, who is interested in implant dentistry, should seriously think about attending these courses.

The best continuing education training programs in implant dentistry are offered by dental schools through out the United States. These programs are spread over a few months (usually about 300 CE hours or more) and all aspects of implant dentistry from A – Z are covered.
Faculties are periodontists, oral surgeons, prosthodontists and general dentists. And, they will tell you at the end of these programs, that you should not take on certain implant cases due to level of difficulty or possibility of complication. Keep in mind that a poorly done endodontic case, can easily be corrected by retreatment or apical micro-surgery. A poorly done implant case, is very very difficult and sometimes impossible to correct.

From a legal point of view,when a general dentist begins to perform procedures that are primarily performed by specialists, the law holds them to the standard of care, expected of specialists providing similar procedures on a regular basis.
Before you sign up for one of these implant training or mentorship courses, stop and think. Would you have an implant done on yourself or a loved one by a dentist that had training for 2-3 days?

I welcome your comments.

Robert Salehrabi, DDS

Thursday, March 3, 2011


Did you know that 70% of Americans are afraid of root canals?

Root canal treatment allows patients to save their natural teeth. The endodontists at Superstition Springs Endodontics are partners with general dentists in helping to save natural teeth. Modern, microscopic endodontic treatment can be a relaxing and pain-free experience.

In a recent AAE survey, 76 percent of participants said they would prefer a root canal to tooth extraction.

Nearly a third would not sell a healthy front tooth for any amount of money.

Most people are not aware that root canal treatment is a viable alternative to tooth extraction

Despite great progress in modern endodontic therapy, there are still misunderstandings about root canal treatment.

Myth #1: Root canal treatment is painful.
Myth #2: Root canal treatment causes illness. (focal infection theory still persists today!)
Myth #3: A good alternative to root canal treatment is extraction.


Friday, February 18, 2011

Cone Beam Computed Tomography (CBCT): A Proper Introduction

At Superstition Springs Endodontics (SSE), we have recently integrated Cone Beam Computed Tomography (CBCT) into our practice of endodontics . In my opinion, CBCT is the future of endodontics and the applications in endodontics seem almost limitless. For this reason, we have chosen to implement this technology into our practice.

However, here are a few basic principles about CBCT that might be helpful.

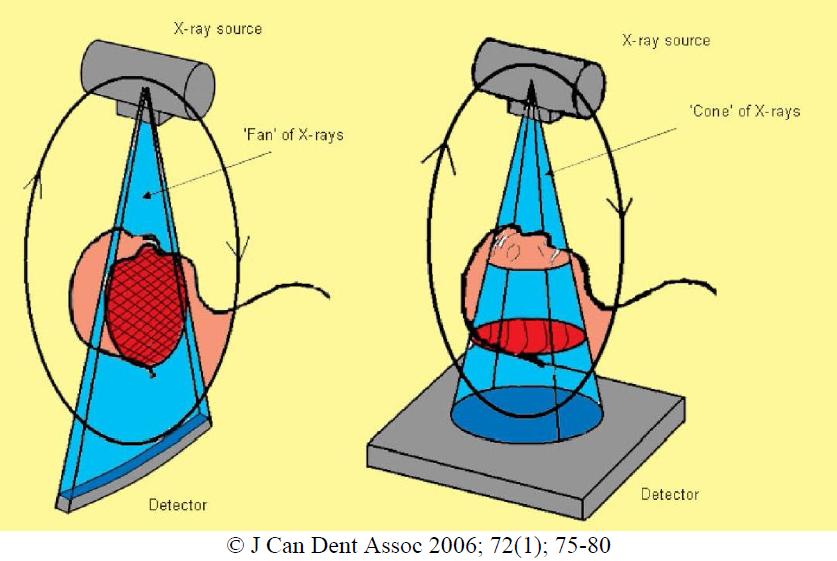
Traditional Computed Tomography (CT or CAT Scan), uses a linear detector and a fan shaped X-ray beam (diagram on left). The detector spins around the patient multiple times over the area to be scan. The computer then takes all of these slices and puts them back together into a 3D image. CT scans are very effective at differentiating between soft and hard tissues.

With Cone Beam Computed Tomography (CBCT), a large detector is used, a cone shaped X ray beam is used, and all data is gathered in a single pass (diagram on right).

This makes the CBCT a smaller unit with the ability to focus the radiographic exam, a single pass around the patient, less radiation exposure and less costly procedure.
CBCT is most effective at evaluation of hard tissues. An important fact to point out is that radiation exposure with CBCT in general is significantly less than traditional CT. Some CBCT units have reduced the radiation exposed to a fraction of the amount of traditional CT.

The field of view (FOV) is an important factor in selecting a CBCT. CBCT has the ability to take a large FOV (full skull), medium FOV (Mx & Md) or focused field (quadrant).

A voxel is a 3 dimensional pixel. The resolution of a CBCT image is determined by the voxel size, as well as the unit's ability to gather & interpret the data with minimal interference/noise.

CBCT units with smaller voxel size are more effective for applications in endodontics, allowing us to see the detail needed.


There have been concerns about the additional radiation exposure associated with CBCT. For the reasons described above, the focus field CBCT has a fraction of the radiation exposure associated with traditional CT. Here are the numbers on radiation...

Since radiation affects different body tissues differently, an effective dose compares the radiation dosage on different body parts on an equivilant basis. The unit for effective dose is the sievert (Sv) joules/kilogram.

In medical procedures, the millisievert (mSv) is used to measure the effective dose.

We are all exposed to about 3.0 mSv/year of natural radiation. Natural radiation comes from the earth as well as from the atmosphere/space.

The following table shows the radiation exposure from several dental radiographic sources as well as medical CT and environmental exposure.

An average American receives 0.0082mSv per day in normal background radiation.

As you can see, one periapical film with d-speed film exposes a patient to 0.0095mSv (which is the equal to about 1.1 days of natural radiation).

A digital periapical film exposes a patient to 1/3 the amount of radiation, 0.0032mSv (which is the equal to about 0.36 days of natural radiation).

The radiation exposure of several CBCT units is listed below.

The amount of radiation exposure is minimal. As with any diagnostic radiographic image, we must balance the need for the information vs. the potential harmful effects of radiation.

The radiation level associated with a CBCT at SSE is the lowest radiation level of any dental CBCT currently available on the market.

Some have inquired into which CBCT that we are using at Superstition Springs Endodontics. We selected the Veraviewepocs 3De by J. Morita. The features we like about it are its high resolution, fast speed, panorex feature, low radiation level and ease of use.

Since many of you will not be able to visit our office to see this in action, the following video clip shows the ease of use and speed of our CBCT.


The following video clip also shows some of the additional benefits of CBCT.


If you are in the Phoenix east valley, we would invite you to contact Annette at our office to schedule a "lunch & learn" and CBCT demonstration (annette@superendo or 480 807-8022). This would include a live demonstration and introduction on how to read a CBCT scan.

If you are in the Phoenix area and would like more information regarding J. Morita or any other CBCT systems (Sirona, Instrumentarium, Soradex, Planmeca or NewTom), contact Jordan at (jordanlhales@gmail.com or 480 227-0435). He will get you any product information for your review.

Tuesday, February 1, 2011

Pulpal Regeneration - More Evidence

In previous posts regarding pulpal regeneration, we have shown not only apical closure, but some dentinal bridging coronal to the apex. While difficult to believe, we have also seen teeth become responsive once again to electric pulp testing. The tissue that forms during pulpal regeneration has been described as "pulp-like", which includes some kind of innervation.

The following case was re-evaluated at 1 year using CBCT. The ability to evaluate apical closure in 3 dimensions is a new way of evaluating success of apexification/apexigenesis/regenerative procedures.

The following case was previously reported and includes the CBCT follow up.


Apical closure at 6 months is noted in regular films.

1 yr recall using CBCT not only shows the apical closure, but coronal bridging under the MTA barrier. In this case a collagen plug was placed prior to MTA. This accounts for the space between the MTA and the new dentinal bridging.

A sagittal view of the tooth also shows complete apical closure as well as coronal dentinal bridging. In this particular case, the MTA plug was not placed deep enough below the enamel and staining occurred, despite using white MTA.

The teeth responded to electric pulp testing with the following readings
#7 - 31 & 36
#8 - 42 &38
#9 - 29
#10 - 28

We recently completed internal bleaching. We removed the MTA down to the layer of collagen plug. Staining noted at the WMTA-dentin barrier. We mechanically removed as much of stain as possible, placed a new coronal barrier and then bleached with the Ultradent endodontic bleaching product. The tooth now looks great. (Sorry no photos on this part)

Wednesday, January 19, 2011

CBCT as a Tool in Endodontic Diagnosis

Cone Beam Computed Tomography (CBCT) is a valuable tool in endodontic diagnosis. The following case illustrates how CBCT provides added diagnostic information not available through traditional 2D imaging.

This patient was referred to our office today after a long week of infection and diagnostic dilemmas. Here's the story...

10 days ago with an ear ache.
9 days ago pt reports pain to chewing & closing teeth together.
8 days ago swelling began. Pt went to ER and was given zithromax, ibuprofen & tylenol #3.
7 days ago swelling increased under tongue and into face.
5 days ago, pt returned to ER where they did a CT scan and found nothing. Pt reports numbness in lip. Pt admitted to hospital and given IV clindamycin. MRI done and "something was found in lower left jaw". Pt started 300mg clindamycin.
Today, patient referred from oral surgery for endodontic consult/vitality testing. Here's how he looked.


Radiographs fairly inconclusive. #18, #19, #20, #21 all normal to percussion, probing and thermal testing.

A small crack noted on the distal marginal ridge of #18. Thermal testing once again indicates a vital pulp. Typically, we would expect a necrotic tooth to be the source of the submandibular swelling that this patient has experienced.

Since tooth #18 is responding normally to thermal testing, we decided to take a CBCT to look for more evidence of the source of infection.

This coronal slice (.25mm) shows radiolucency around the distal root #18. This image is more conclusive than the standard 2D image.

A sagittal slice through the distal root of #18 shows the lesion and its perforation of the lingual plate.

An axial view of the distal root of #18 also shows perforation to the lingual.

These CBCT slices are conclusive enough to revise the pulpal diagnosis to "partially necrotic" and recommend endodontic treatment. It appears that the distal root is necrotic and the infection is spreading through the lingual plate.


RCT initiated. Upon access, we find vital pulp tissue in the mesial canals, and necrotic pulp tissue in the distal canal.

Further removal of the distal crack finds the crack extending down the distal root, below the CEJ. Extraction is recommended.

In endodontic diagnostics, we typically classify pulpal status as:

1. Normal
2. Reversibly Inflammed
3. Irreversibly Inflammed
4. Necrotic

However, things are not always a cut an dry as that. This case illustrates that "partially necrotic" pulp is a possible classification of pulpal status.

Following removal of the tooth, the infection quickly resolved.

CBCT is an important tool for diagnostic imaging in endodontics.

Monday, December 27, 2010

CBCT to Evaluate Internal Root Resorption

CBCT can be used to evaluate the extent of root resorption. Before this technology, we would have to excavate a resorptive defect to evaluated the extent and restorability. The CBCT allows us to see in all dimensions the extent of a resorptive defect. In this case, the non-restorability was determined with CBCT alone. This saves the patient and clinician time and money.

This video is made of individuals slices 1.0mm thick with 0.25mm interval between each slice.

Thursday, December 16, 2010